


Forget most of what you know about using the Internet. Think instead about communities and families living across a region, and imagine how electronic healthcare services would support them.

Today, the focus is increasingly on understanding the dynamics across multiple health agencies and developing an architectural information and communications technology (ICT) response. In this context, ICT architecture refers to the process of determining the principal design attributes associated with connecting people, entities, and services in a planned manner in order to optimize delivery, cost, and scalability. Significant activity is occurring in many regions and countries. The capability of ICT to be transformative1, particularly in terms of system efficiency, is not disputed2 and often claims to provide tangible benefits in specific areas such as health.3
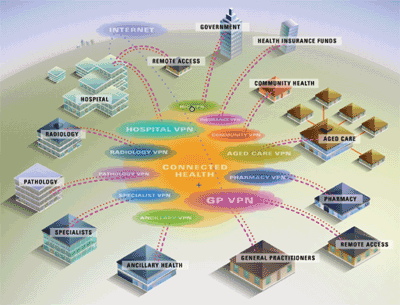 In the European Commission report (titled ‘National Strategy for e-Health’) an evaluation of 10 e-health case studies yielded the observation that – “given the right approach, context, and implementation process, ICT-based solutions can indeed improve the quality, access and efficiency of healthcare provision”. However, realisation of actual and tangible benefits happen only after couple of years. In this context, it may be worthwhile to highlight a study by RAND Corporation, which modelled the impact of EMR adoption in United States and found the potential benefit in monetary terms to be as much as US$ 77 billion per year.4

People live in places and move across geographic areas. In doing so, they tend to form identifiable communities. Mixed in among these communities are general practitioners, specialists, pathologists, radiologists, elder-care facilities, community health services and hospitals. People needing care regularly move through a geographic area seeking support and treatment. Patients are discharged from hospitals, sometimes requiring ongoing care from a general practitioner. Elderly patients and/or chronic-care patients may move between facilities and may require a wide variety of medical providers over extended periods.

It has been observed that most health activity happens in the community, and not in the hospital. Health systems tend to be acute-centric and as such, ignore the burden of care required in a community setting, particularly for chronic-care patients. When primary care fails, the demand increases on ambulatory system, such as outpatient care. This increase can cause failures in the outpatient system, resulting in more hospital admissions.

This scenario is the foundation for two emerging concepts. The first is that health-related information and services need to be available and accessible throughout a region and across all patient and health provider segments, if quality, safety, and inclusivity have to be equitable. Information availability and accessibility are directly tied to significant, positive and improved health outcomes.5 The second concept is that a systemic failure in one part of the health system can have major ramifications on other parts of the system. This is because costs tend to be high in the hospital and low in the community and systemic failures magnify cost, often exponentially. Put another way, errors and mismanagement cost much more to recover at the hospital end than at the community end of the care spectrum, yet relatively little effort is expended to improve community care. Think of it this way – an inpatient admission represents a failure of ambulatory management.

Patients and their families “move” through regional, state or national health systems. The efficiency and effectiveness of their “journey” bear directly on improved health outcomes. This is, for example, reflected in a reduction in waiting time for emergency treatment or surgery, or in reduced admission rates for diabetes sufferers because of improved case management. This journey also impacts how families and individuals seek medical support, particularly in chronic-care areas. Mental health is typical among these.
The fundamental proposition is that providers and patients need to connect in a timely and appropriate manner. That connection via electronic means is the primary opportunity given the principles of a patient’s journey, which can start at his or her home, neighbourhood or village